


Indicated for treatment of bleeding episodes and perioperative management in adults and children with hemophilia A or B with inhibitors, congenital factor VII (FVII) deficiency, Glanzmann’s thrombasthenia with refractoriness to platelet transfusions, and in adults with acquired hemophilia.
NovoSeven® RT is the only rFVIIa approved for congenital hemophilia A or B with inhibitors across all age groups and boasts 35+ years of clinical safety and efficacy data.1-3
CHAwI=congenital hemophilia A with inhibitors.
Efficacy seen in Lusher et al4
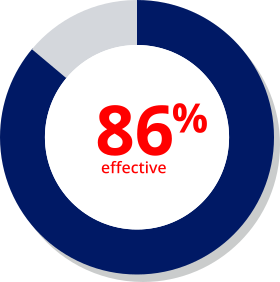
Muscle bleeds
N=29
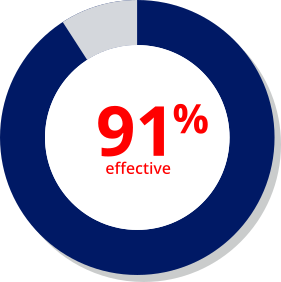
Joint bleeds
N=144

Efficacy seen in adept™25
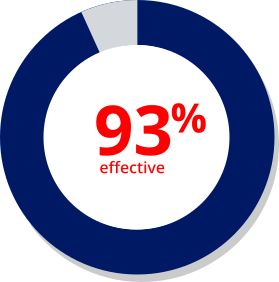
All bleed locations at 12 hours
N=69
Consistent efficacy seen in joint, target joint, mucocutaneous, muscle, and other bleeding episodes.
98% effective bleed control in patients ≤18 years, based on real-world experience.6
Based on a retrospective analysis of the HTRS Registry data that evaluated treatment of bleeding episodes in patients with inhibitors, including 284 children aged ≤18 years, treated with NovoSeven® RT between January 2004 and November 2008. Efficacy reflects number of patients with outcome reported as bleeding stopped or slowed.6
NovoSeven® RT controls joint bleeds fast1,4,7,a
Your patients expect fast resolution of joint bleeds. NovoSeven® RT controls bleeds in as few as 5 hours with a median of 2 doses.4,7,b

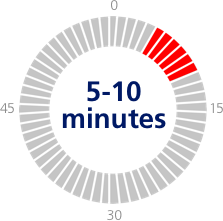
Quickly achieves maximum activity
NovoSeven® RT achieved maximum activity within 5-10 minutes of infusion.7,c
NovoSeven® RT can be readministered as quickly as every 2 hours compared with 6 to 12 hours for FEIBA®.1,8
aIn patients with hemophilia A or B with inhibitors.4
bCalculation of 5 hours is based on 2.2 doses at 2-hour interval.
cFVIIa activity IU/mL.
FVIIa=activated Factor VII; HTRS=Hemostasis & Thrombosis Research Society.
Effectiveness in surgeries and procedures
NovoSeven® RT is the only bypassing agent approved for continuous infusion and with controlled clinical trials supporting its efficacy during and after surgery in patients with CHwI.1,2,8,11,d
The only rFVIIa approved for surgery in children and adults1,2,e
Bleed protection in major and minor surgeries in CHwI11,d,f
Major surgeries

Minor surgeries
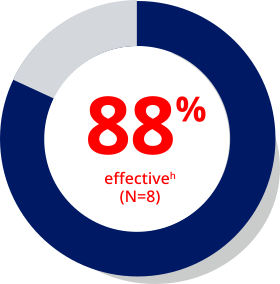
Results of a prospective, randomized trial show the effectiveness of NovoSeven® RT. Percentage of patients with adequate hemostasis11,f:




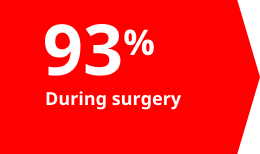



The postoperative period: essential to surgical success.
Adapted from Shapiro et al.11,d
dIn patients with hemophilia A or B with inhibitors. Actual length of postoperative period may vary. Charts show results from 90 mcg/kg dose only.
eUse in acquired hemophilia is indicated for adults only.
fData from a prospective, randomized trial comparing 35 mcg/kg with 90 mcg/kg rFVIIa, each given before surgery, every 2 hours intraoperatively as needed and in the first 48 hours postoperatively, then every 2 to 6 hours through postoperative Day 3. Beyond Day 5, patients were treated with open-label 90 mcg/kg until discharge at the discretion of the investigator. A total of 29 patients underwent 11 major and 18 minor procedures.11
gProcedures included synovectomy, hip arthroplasty, knee joint manipulation, knee cartilage repair, bone graft, and laparoscopic renal biopsy.11
hProcedures included placement of central venous catheters and other venous access devices, and removal of a venous access device.11
CHwI=congenital hemophilia A with inhibitors; rFVIIa=recombinant activated Factor VII.
Established safety profile
Pivotal studies and real-world data show a low rate of thrombotic events
Serious arterial and venous thrombotic events have been reported in clinical trials and postmarketing surveillance.1 Thrombotic adverse reactions in pivotal clinical trials occurred in 0.2% of bleeding episodes in patients with congenital hemophilia with inhibitors.1
Data from pivotal clinical trials1
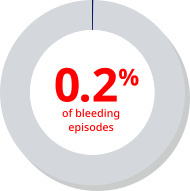
Occurrence of thrombotic events
NovoSeven® RT is the only rFVIIa that was used in the Hemlibra® pivotal clinical trials.
NovoSeven® RT was used in 61 patients with CHAwI treated with Hemlibra® in 3 separate pivotal trials: HAVEN1, HAVEN2, and HAVEN4.10,12,i
- 180 bleeds were treated with NovoSeven® RT only in HAVEN1.
- No SAEs, TMAs, or TEs were observed with use of NovoSeven® RT alone in HAVEN1, HAVEN2, and HAVEN4.
- No new or unexpected safety concerns were observed with use of NovoSeven® RT in conjunction with Hemlibra®.
- Two cases of TMA occurred in patients treating with Hemlibra® while receiving FEIBA® and NovoSeven® RT. Simultaneous use of Hemlibra® and FEIBA® should be avoided.

MASAC recommends rFVIIa as a first option to treat acute bleeding episodes in patients with CHAwI on emicizumab—aPCC should be avoided if possible.9
iThe analysis included bleeding episodes in the HAVEN1, HAVEN2, and HAVEN4 clinical trials for which patients with CHAwI on emicizumab prophylaxis (at the labeled dose) used rFVIIa. Initial individual dosing with rFVIIa, dosing intervals, and cumulative dosing were evaluated. All adverse events reported in each of the 3 trials, including available narratives, were assessed. The cutoff dates for the data presented were for HAVEN1 (primary analysis) September 2017, HAVEN2 (interim analysis) October 2017, and HAVEN4 (primary analysis) December 2017.10
aPCC=activated prothrombin complex concentrate; MASAC=Medical and Scientific Advisory Council; SAE=serious adverse event; TE=thrombotic event; TMA=thrombotic microangiopathy.
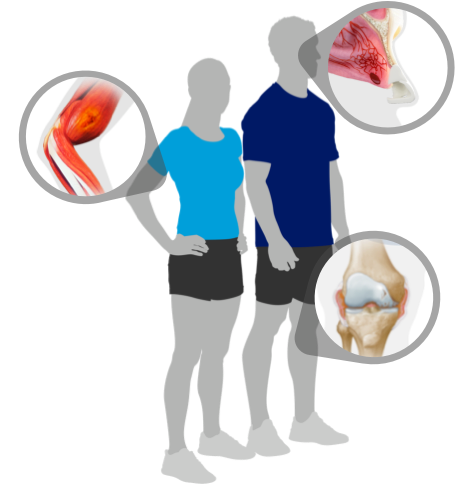
Teach patients the signs and symptoms of internal bleeds
This educational resource may be able to help your patients quickly identify bleeds when and where they happen. Use this tool to help your patients learn to identify breakthrough bleeds which may require treatment on-the-go.
Study design
Randomized, double-blind, parallel group, international multicenter trial
Patients randomized: Patients with hemophilia A or B with or without inhibitors (N=84).
Study design: Patients were given NovoSeven® RT 35 or 70 mcg/kg at dosing intervals of 2 to 3 hours. Efficacy reflects number of patients in 70 mcg/kg group reporting excellent, effective, or partially effective results. Response was rated as “excellent” if patient demonstrated definitive relief of pain/tenderness and/or if there was a measurable decrease in the size of the bleed (or arrest of bleeding) in 8 hours or less. An “effective” response was measured by any of these 3 events occurring from 8 to 14 hours; a “partially effective” response either occurred after 14 hours or indicated detectable relief of pain/tenderness or decrease in size of the hemorrhage or if the bleeding had slowed.
Primary endpoint: Comparing the efficacy between 2 different doses of NovoSeven® RT in the treatment of patients with hemophilia A or B, with or without inhibitors, for the treatment of joint, muscle, and mucocutaneous bleeds.
Secondary endpoint: Compare short-term safety between 2 doses of NovoSeven® RT and monitor patients for the development of inhibitors to NovoSeven® RT and to any contaminants included in the preparation of NovoSeven® RT.
adept™2 phase 3 trial
Patients randomized: Patients ≥12 years of age with hemophilia A with inhibitors (N=66) or hemophilia B with inhibitors (N=6) who have experienced at least 5 bleeds during treatment prior to entering the trial.
Study design: A 12-month, international, multicenter, randomized, double-blind, active-controlled, crossover, confirmatory phase 3 trial. Primarily done in the home setting, treatments of bleeding episodes were randomized, either treated with 1 to 3 doses of vatreptacog alfa (340 bleeding episodes) at 80 mcg/kg or 1 to 3 doses of NovoSeven® RT (227 bleeding episodes) at 90 mcg/kg.
Primary endpoint: Effective bleed control, which was defined as no additional hemostatic treatment needed (other than the original medication) within 12 hours after first dose.
Secondary endpoint: Effective and sustained bleed control at 1 and 2 days after initial dose, number of doses of trial product for each bleed, and changes in pain assessment.
Randomized, double-blind bioequivalence trial
Patients randomized: Healthy participants ages 18-45 (N=22).
Study design: A single-center, randomized, double-blind, two-way crossover study. Participants received 1 intravenous bolus injection each of NovoSeven® RT and NovoSeven®. Both bolus injections were 90 mcg/kg and occurred 2 to 3 weeks apart at consecutive visits. While the comparison is not shown for FVIIa, activity for NovoSeven® RT was the bioequivalent range of that for NovoSeven® during this period.
Primary endpoint: Demonstrate bioequivalence between NovoSeven® and a new formulation, stable up to 77 °F.
Secondary endpoint: Comparing the area under the plasma activity time curve and the mean residence time between NovoSeven® and the new formulation.
Prospective, randomized trial evaluating efficacy in surgery
Patients randomized: Patients with hemophilia A with inhibitors (N=25), hemophilia B with inhibitors (N=3), and acquired hemophilia (N=1).
Study design: This trial compared 35 mcg/kg with 90 mcg/kg rFVIIa. Patients with inhibitors (FVIII, N=26; FIX, N=3) were given NovoSeven® RT immediately prior to incision, then every 2 hours intraoperatively or as needed, followed by every 2 hours from wound closure in the first 48 hours, then every 2 to 6 hours through Day 3. Beyond Day 5, patients were treated with open-label 90 mcg/kg until discharge at the discretion of the investigator. A total of 29 patients underwent 11 major and 18 minor procedures. Data shown are from the 90 mcg/kg group.
Primary endpoint: Demonstrated hemostasis at the surgical site during operation, after the wound is closed, 8 hours after the wound is closed, and once daily for 5 days after the procedure.
Explore how hospitals use NovoSeven® RT to treat CHwI

NovoSeven® RT is manufactured with safety in mind

Find resources that can help your patients with ultra-rare bleeding disorders
Important Safety Information for NovoSeven® RT
WARNING: THROMBOSIS
- Serious arterial and venous thrombotic events following administration of NovoSeven® RT have been reported
- Discuss the risks and explain the signs and symptoms of thrombotic and thromboembolic events to patients who will receive NovoSeven® RT
- Monitor patients for signs or symptoms of activation of the coagulation system and for thrombosis
Warnings and Precautions
- Serious arterial and venous thrombotic events have been reported in clinical trials and postmarketing surveillance
- Patients with congenital hemophilia receiving concomitant treatment with aPCCs (activated prothrombin complex concentrates), older patients particularly with acquired hemophilia and receiving other hemostatic agents, and patients with a history of cardiac and vascular disease may have an increased risk of developing thrombotic events
- Hypersensitivity reactions, including anaphylaxis, can occur with NovoSeven® RT. Patients with a known hypersensitivity to mouse, hamster, or bovine proteins may be at a higher risk of hypersensitivity reactions. Discontinue infusion and administer appropriate treatment when hypersensitivity reactions occur
- Factor VII deficient patients should be monitored for prothrombin time (PT) and factor VII coagulant activity (FVII:C). If FVII:C fails to reach the expected level, or PT is not corrected, or bleeding is not controlled after treatment with the recommended doses, antibody formation may be suspected and analysis for antibodies should be performed
- Laboratory coagulation parameters (PT/INR, aPTT, FVII:C) have shown no direct correlation to achieving hemostasis
Adverse Reactions
- The most common and serious adverse reactions in clinical trials are thrombotic events. Thrombotic adverse reactions following the administration of NovoSeven® RT in clinical trials occurred in 4% of patients with acquired hemophilia and 0.2% of bleeding episodes in patients with congenital hemophilia
Drug Interactions
- Thrombosis may occur if NovoSeven® RT is administered concomitantly with Coagulation Factor XIII
Please click here for NovoSeven® RT Prescribing Information, including Boxed Warning.
Indications and Usage
NovoSeven® RT (coagulation Factor VIIa, recombinant) is a coagulation factor indicated for:
- Treatment of bleeding episodes and perioperative management in adults and children with hemophilia A or B with inhibitors, congenital Factor VII (FVII) deficiency, and Glanzmann’s thrombasthenia with refractoriness to platelet transfusions, with or without antibodies to platelets
- Treatment of bleeding episodes and perioperative management in adults with acquired hemophilia
Important Safety Information for NovoSeven® RT
WARNING: THROMBOSIS
- Serious arterial and venous thrombotic events following administration of NovoSeven® RT have been reported
- Discuss the risks and explain the signs and symptoms of thrombotic and thromboembolic events to patients who will receive NovoSeven® RT
- Monitor patients for signs or symptoms of activation of the coagulation system and for thrombosis
Warnings and Precautions
- Serious arterial and venous thrombotic events have been reported in clinical trials and postmarketing surveillance
- Patients with congenital hemophilia receiving concomitant treatment with aPCCs (activated prothrombin complex concentrates), older patients particularly with acquired hemophilia and receiving other hemostatic agents, and patients with a history of cardiac and vascular disease may have an increased risk of developing thrombotic events
- Hypersensitivity reactions, including anaphylaxis, can occur with NovoSeven® RT. Patients with a known hypersensitivity to mouse, hamster, or bovine proteins may be at a higher risk of hypersensitivity reactions. Discontinue infusion and administer appropriate treatment when hypersensitivity reactions occur
- Factor VII deficient patients should be monitored for prothrombin time (PT) and factor VII coagulant activity (FVII:C). If FVII:C fails to reach the expected level, or PT is not corrected, or bleeding is not controlled after treatment with the recommended doses, antibody formation may be suspected and analysis for antibodies should be performed
- Laboratory coagulation parameters (PT/INR, aPTT, FVII:C) have shown no direct correlation to achieving hemostasis
Adverse Reactions
- The most common and serious adverse reactions in clinical trials are thrombotic events. Thrombotic adverse reactions following the administration of NovoSeven® RT in clinical trials occurred in 4% of patients with acquired hemophilia and 0.2% of bleeding episodes in patients with congenital hemophilia
Drug Interactions
- Thrombosis may occur if NovoSeven® RT is administered concomitantly with Coagulation Factor XIII
Please click here for NovoSeven® RT Prescribing Information, including Boxed Warning.
Indications and Usage
NovoSeven® RT (coagulation Factor VIIa, recombinant) is a coagulation factor indicated for:
- Treatment of bleeding episodes and perioperative management in adults and children with hemophilia A or B with inhibitors, congenital Factor VII (FVII) deficiency, and Glanzmann’s thrombasthenia with refractoriness to platelet transfusions, with or without antibodies to platelets
- Treatment of bleeding episodes and perioperative management in adults with acquired hemophilia
References
- NovoSeven RT [package insert]. Plainsboro, NJ; Novo Nordisk Inc.
- SEVENFACT. Package insert. HEMA Biologics; 2025.
- Hedner U. History of rFVIIa therapy. Thromb Res. 2010;125(suppl 1):s4-s6.
- Lusher JM, Roberts HR, Davignon G, et al; rFVIIa Study Group. A randomized, double-blind comparison of two dosage levels of recombinant factor VIIa in the treatment of joint, muscle and mucocutaneous haemorrhages in persons with haemophilia A and B, with and without inhibitors. Haemophilia. 1998;4(6):790-798.
- Lentz SR, Ehrenforth S, Abdul Karim F, et al; adept™2 investigators. Recombinant factor VIIa analog in the management of hemophilia with inhibitors: results from a multicenter, randomized, controlled trial of vatreptacog alfa. J Thromb Haemost. 2014;12(8):1244-1253.
- Neufeld EJ, Saxena K, Kessler CM, Cooper DL; HTRS Investigators. Dosing, efficacy, and safety of recombinant factor VIIa (rFVIIa) in pediatric versus adult patients: the experience of the Hemostasis and Thrombosis Research Society (HTRS) Registry (2004-2008). Pediatr Blood Cancer. 2013;60(7):1178-1183.
- Bysted BV, Scharling B, Møller T, Hansen BL. A randomized, double-blind trial demonstrating bioequivalence of the current recombinant activated factor VII formulation and a new robust 25°C stable formulation. Haemophilia. 2007;13(5):527-532.
- FEIBA. Package insert. Takeda Pharmaceuticals U.S.A., Inc; 2024.
- National Hemophilia Foundation. Recommendation on the use and management of emicizumab-kxwh (Hemlibra®) for hemophilia A with and without inhibitors (MASAC Document #268). April 27, 2022. Accessed October 21, 2025. https://www.bleeding.org/sites/default/files/document/files/268_Emicizumab.pdf
- Levy GG, Asikanius E, Kuebler P, Benchikh El Fegoun S, Esbjerg S, Seremetis S. Safety analysis of rFVIIa with emicizumab dosing in congenital hemophilia A with inhibitors: experience from the HAVEN clinical program. J Thromb Haemost. 2019;17(9):1470-1477.
- Shapiro AD, Gilchrist GS, Hoots WK, Cooper HA, Gastineau DA. Prospective, randomised trial of two doses of rFVIIa (NovoSeven) in haemophilia patients with inhibitors undergoing surgery. Thromb Haemost. 1998;80(5):773-778.
- Oldenburg J, Mahlangu JN, Kim B, et al. Emicizumab prophylaxis in hemophilia A with inhibitors. N Engl J Med. 2017;377(9):809-818 and appendix.